broad free population screening program is recommended for average-risk adults.
Hard to detect, easy to miss
Pancreatic cancer detection is about risk, symptoms and the right scan at the right time.
There is no proven broad population screening program for average-risk people. The best current strategy is high-risk surveillance for selected families and gene carriers, urgent workup of jaundice or weight loss, and careful use of CT, MRI/MRCP, EUS and biopsy.
families and gene carriers may benefit from MRI/MRCP and EUS surveillance.
imaging, not CA19-9 alone, drives diagnosis and staging.
EUS-guided tissue sampling confirms cancer when tissue is needed.
Brief outline
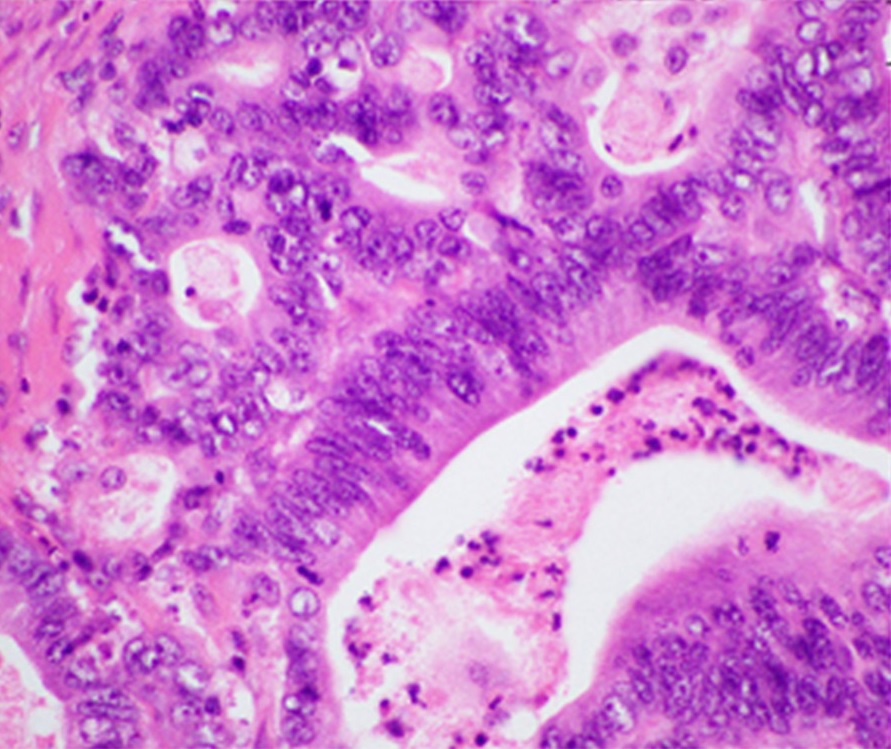
Most pancreatic cancers are ductal adenocarcinomas.
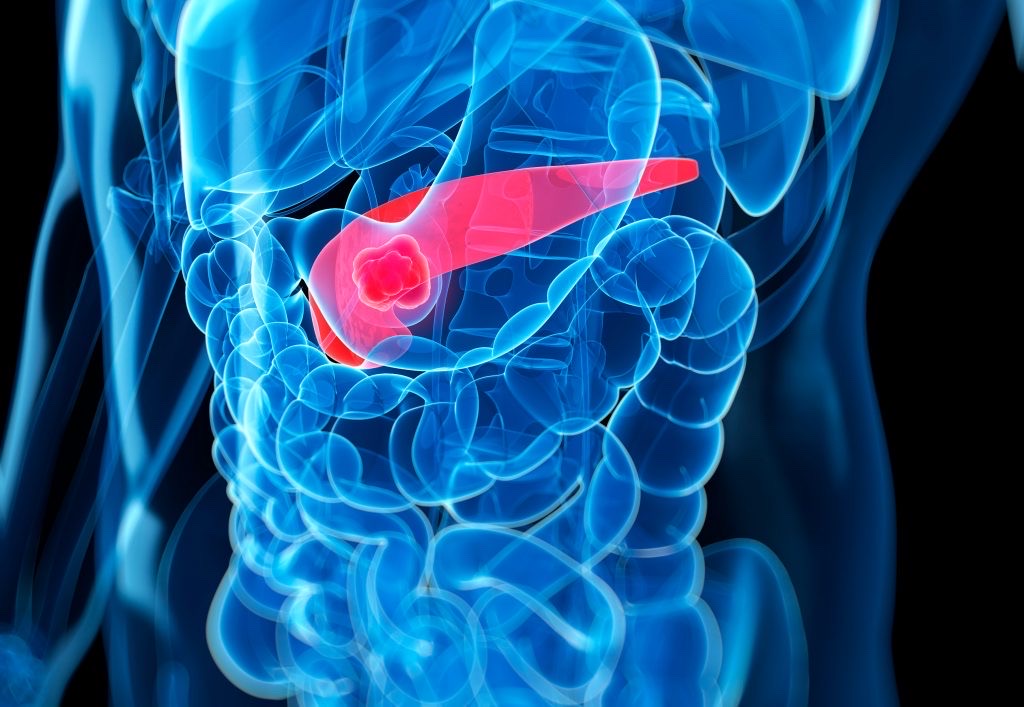
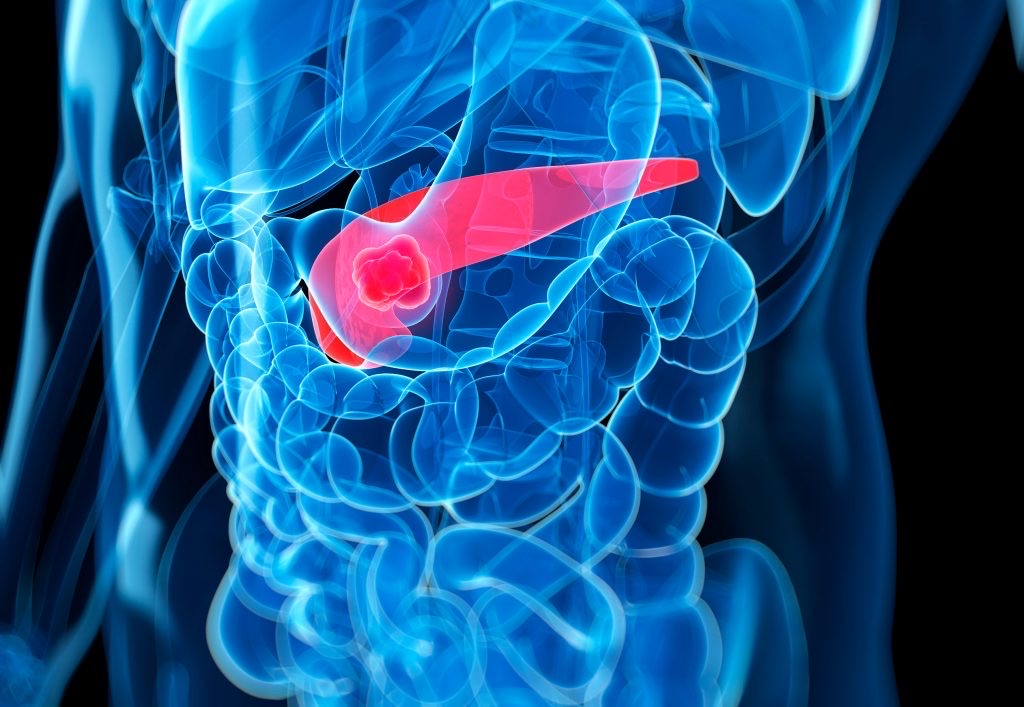
The pancreas sits deep behind the stomach. Early tumors may cause no symptoms until they obstruct the bile duct, invade nerves, cause weight loss or spread. Bile duct cancers, ampullary cancers and gallbladder/biliary obstruction can overlap clinically, especially when jaundice appears. That anatomy is why a simple self-check or routine physical exam does not work.
Demographics and risk factors
Risk rises with age and is higher with smoking, chronic pancreatitis, long-standing diabetes, obesity, heavy alcohol through pancreatitis risk, family history, inherited pathogenic variants and some cystic pancreatic lesions. Many patients have no obvious risk factor.
Inherited risk can involve BRCA1/2, PALB2, ATM, CDKN2A, STK11/Peutz-Jeghers, PRSS1/hereditary pancreatitis, Lynch genes and strong familial pancreatic cancer kindreds.
Do not ignore
The early signals are often vague, but some patterns should move fast.
Who is high-risk?
High-risk surveillance is not the same as average-risk screening.
Screening reality
There is no FIT or mammogram equivalent for average-risk pancreatic cancer.
That is frustrating because pancreatic cancer is exactly the cancer people hope a blood test or whole-body scan will catch. The problem is base rate: in average-risk people the cancer is uncommon, so even a fairly specific test can create many false alarms, scans and biopsies.
MRI/MRCP
Good for ducts and cysts, no radiation, often paired with EUS in surveillance programs.
Endoscopic ultrasound
EUS can see small pancreatic lesions and allows fine needle biopsy, but it is operator-dependent and invasive.
CA19-9
CA19-9 can help monitor known pancreatic cancer, but it is not sensitive or specific enough for general screening. It can rise with jaundice, cholangitis and other cancers, and some people cannot produce it.
Blood multi-cancer tests
Pancreas is a headline promise for MCED tests, but broad use still needs proof of fewer late cancers, fewer deaths and acceptable false positives.
Whole-body MRI
Whole-body MRI might incidentally show a pancreatic mass, liver metastases, duct dilation or cysts, but it is not a proven pancreatic cancer screening program for average-risk people. In high-risk families, targeted pancreas MRI/MRCP and EUS are more standard than a generic scan.
Diagnostic pathway
Symptoms usually lead to blood tests and cross-sectional imaging first.
Cysts and precursors
Many pancreatic cysts are incidental; a minority are dangerous.
Modern CT and MRI find cysts frequently, especially with age. Some are harmless. Others, such as main-duct IPMN, mucinous cystic neoplasm or cysts with high-risk features, can be cancer precursors.
The controversy
Pancreatic cancer is the emotional argument for early detection, but also the statistical trap.
The desire is completely understandable: if a blood test or scan could reliably catch pancreatic cancer before symptoms, it could save lives. But a population test must prove more than detection. It must find treatable disease early enough, avoid huge false-positive cascades, and reduce mortality.
The benefit argument
Pancreatic cancer is often diagnosed late, surgery is possible only for a minority, and high-risk programs can sometimes find precursor lesions or stage I cancers.
The harm argument
Average-risk prevalence is low. False positives can lead to repeated MRI/EUS, biopsy, surgery, pancreatic leaks, diabetes, anxiety and cost.
High-risk surveillance
Genetic/family-history programs concentrate testing where the pre-test probability is higher and expertise is available.
MCED / whole-body MRI
Pancreatic cancer may show up, but incidental cysts, indeterminate lesions and false reassurance are real. Outcome trials matter.
Sources and reviews
Good starting points.
NCI pancreatic screening PDQHigh-risk screening evidence, MRI/MRCP, EUS and limitations.
CAPS Consortium recommendationsInternational consensus on who should undergo pancreatic surveillance and how.
ASGE high-risk screening guidelineEndoscopic ultrasound, MRI and high-risk individual screening recommendations.
American Cancer Society statisticsCurrent US pancreatic cancer incidence and mortality statistics.
NCI pancreatic cancer overviewSymptoms, diagnosis, staging and treatment context.
ClinicalTrials.govEarly detection, biomarker, imaging and surveillance trials.