is the common ultrasound surveillance interval in many HCC programs.
Cirrhosis surveillance, ultrasound, AFP and multiphase imaging
Liver cancer is one of the cancers where surveillance is clearly risk-based.
For cirrhosis and selected hepatitis B groups, surveillance with ultrasound, often with AFP, can find hepatocellular carcinoma earlier. Average-risk screening is not routine.
can help but is not reliable alone.
multiphase arterial enhancement and washout often establish HCC diagnosis.
cirrhosis, hepatitis B/C and other liver disease define who benefits.
Brief outline
Primary liver cancer is usually HCC or cholangiocarcinoma.
Hepatocellular carcinoma arises from liver cells, often in cirrhosis or chronic hepatitis. Cholangiocarcinoma arises from bile ducts and has different risk factors, imaging and markers.
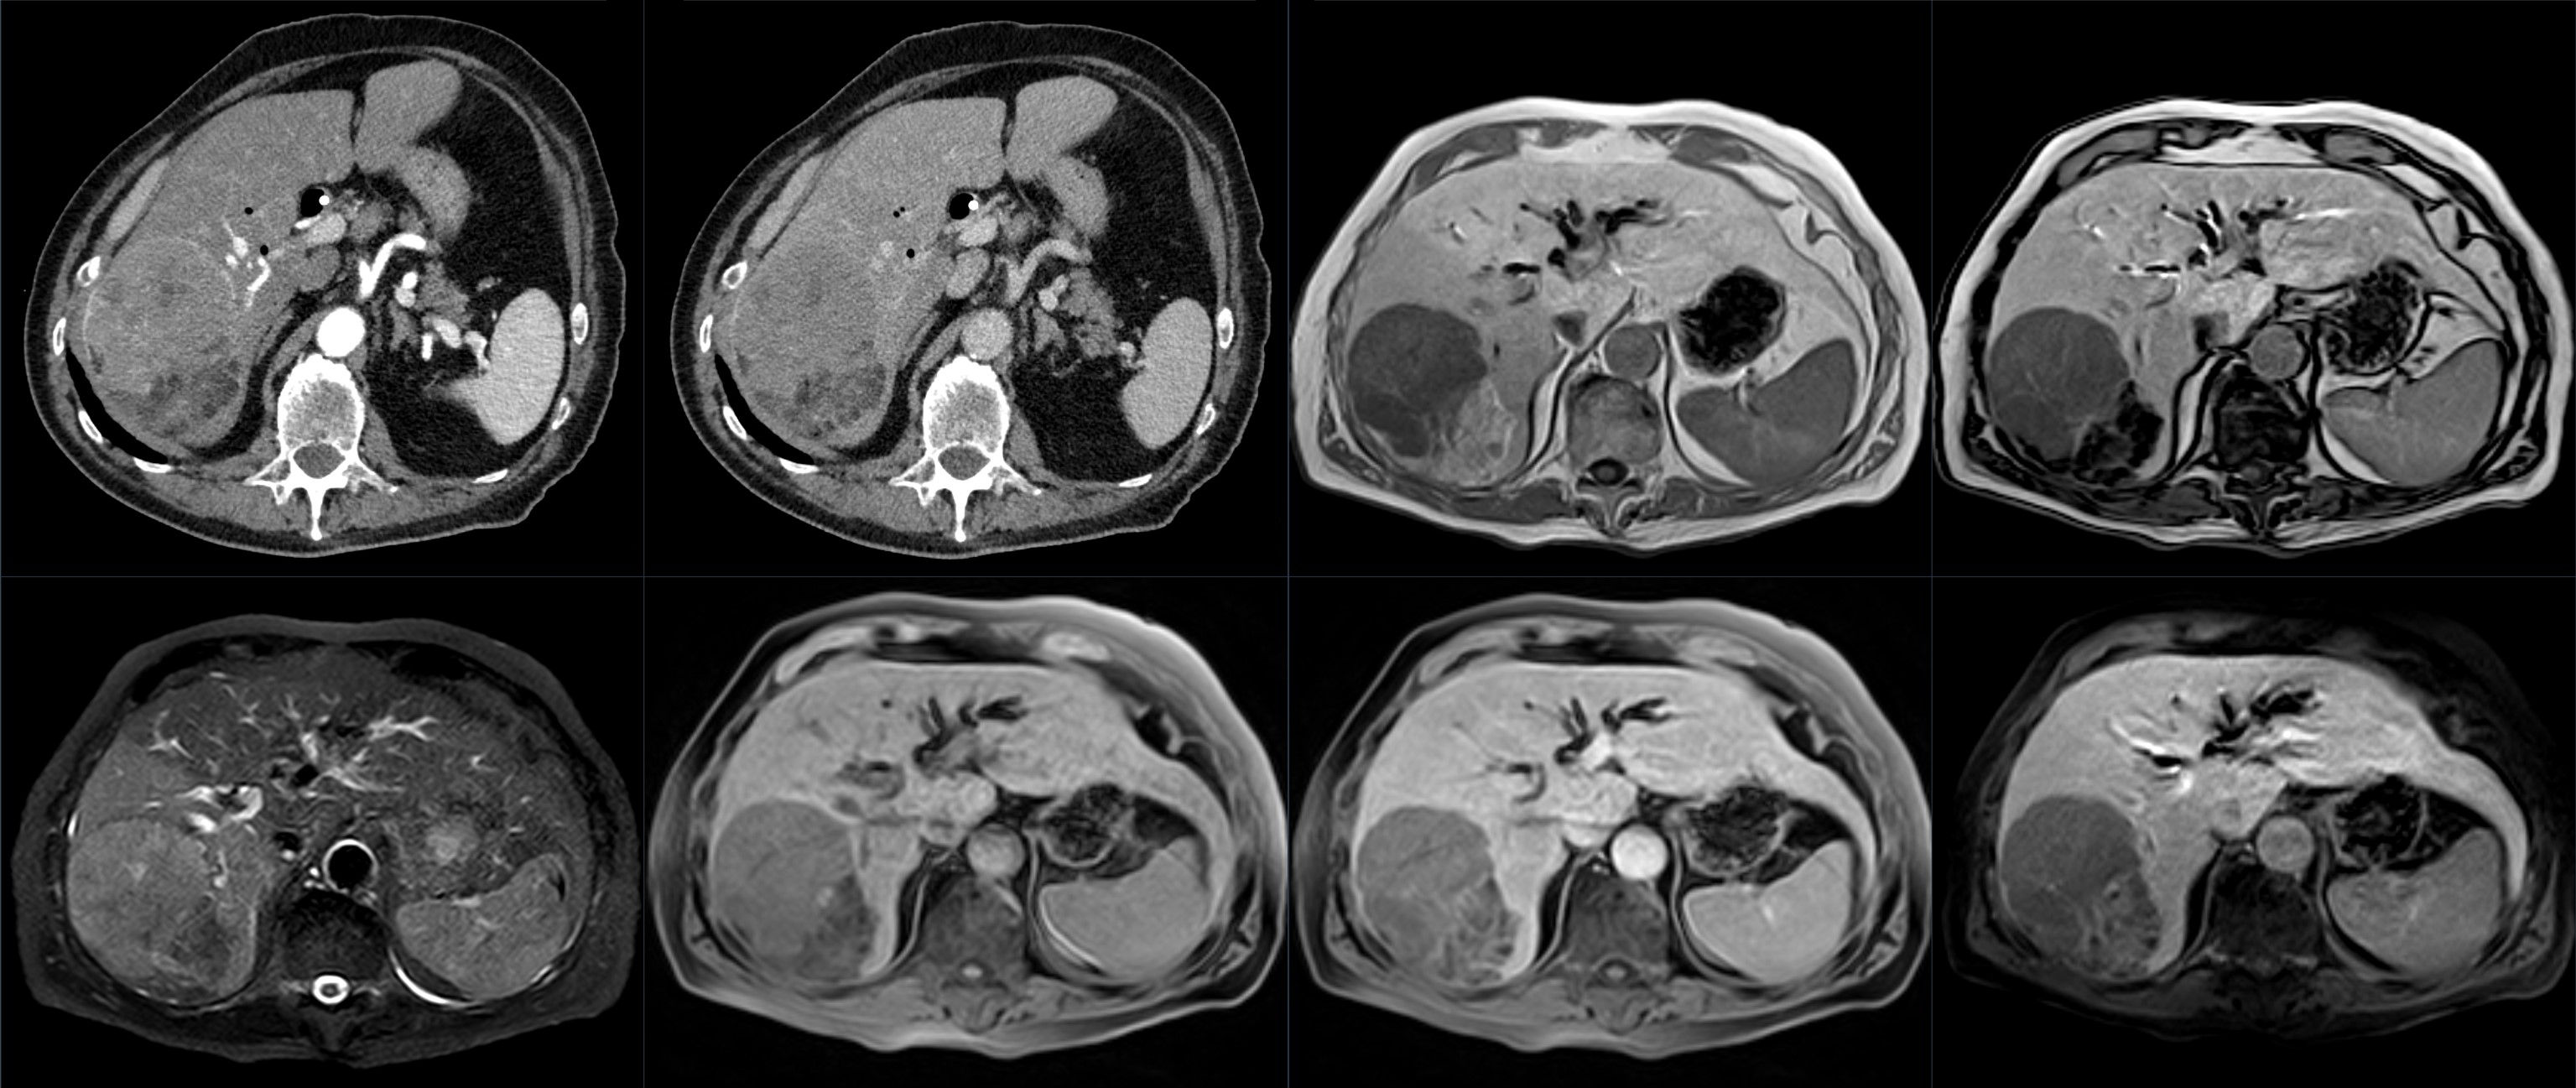
Detection frame
Liver cancer detection is one of the clearest examples of targeted surveillance: test people with enough risk for the signal to be useful, not everyone with a normal liver.
Do not ignore
Symptoms often mean more advanced disease.
Risk and genetics
Cirrhosis and viral hepatitis drive surveillance.
Screening
Surveillance is for high-risk liver disease, not average-risk adults.
Many liver societies recommend ultrasound every 6 months, often with AFP, for cirrhosis and selected hepatitis B groups. Ultrasound quality can be poor in obesity or nodular cirrhosis; CT/MRI alternatives are sometimes considered.
Ultrasound +/- AFP
Usually every 6 months in eligible high-risk people.
AFP
Helpful when rising but not sensitive or specific enough alone.
Multiphase CT
Assesses arterial enhancement, washout, vascular invasion and metastases.
MRI liver protocol
Often more sensitive for small lesions; useful when ultrasound is limited.
Biopsy
Used for indeterminate imaging, non-cirrhotic liver, suspected cholangiocarcinoma or metastasis.
Whole-body MRI
May find liver lesions but cannot replace structured HCC surveillance in known cirrhosis.
Images, labs and tissue
HCC may be diagnosed by imaging pattern, not always biopsy.
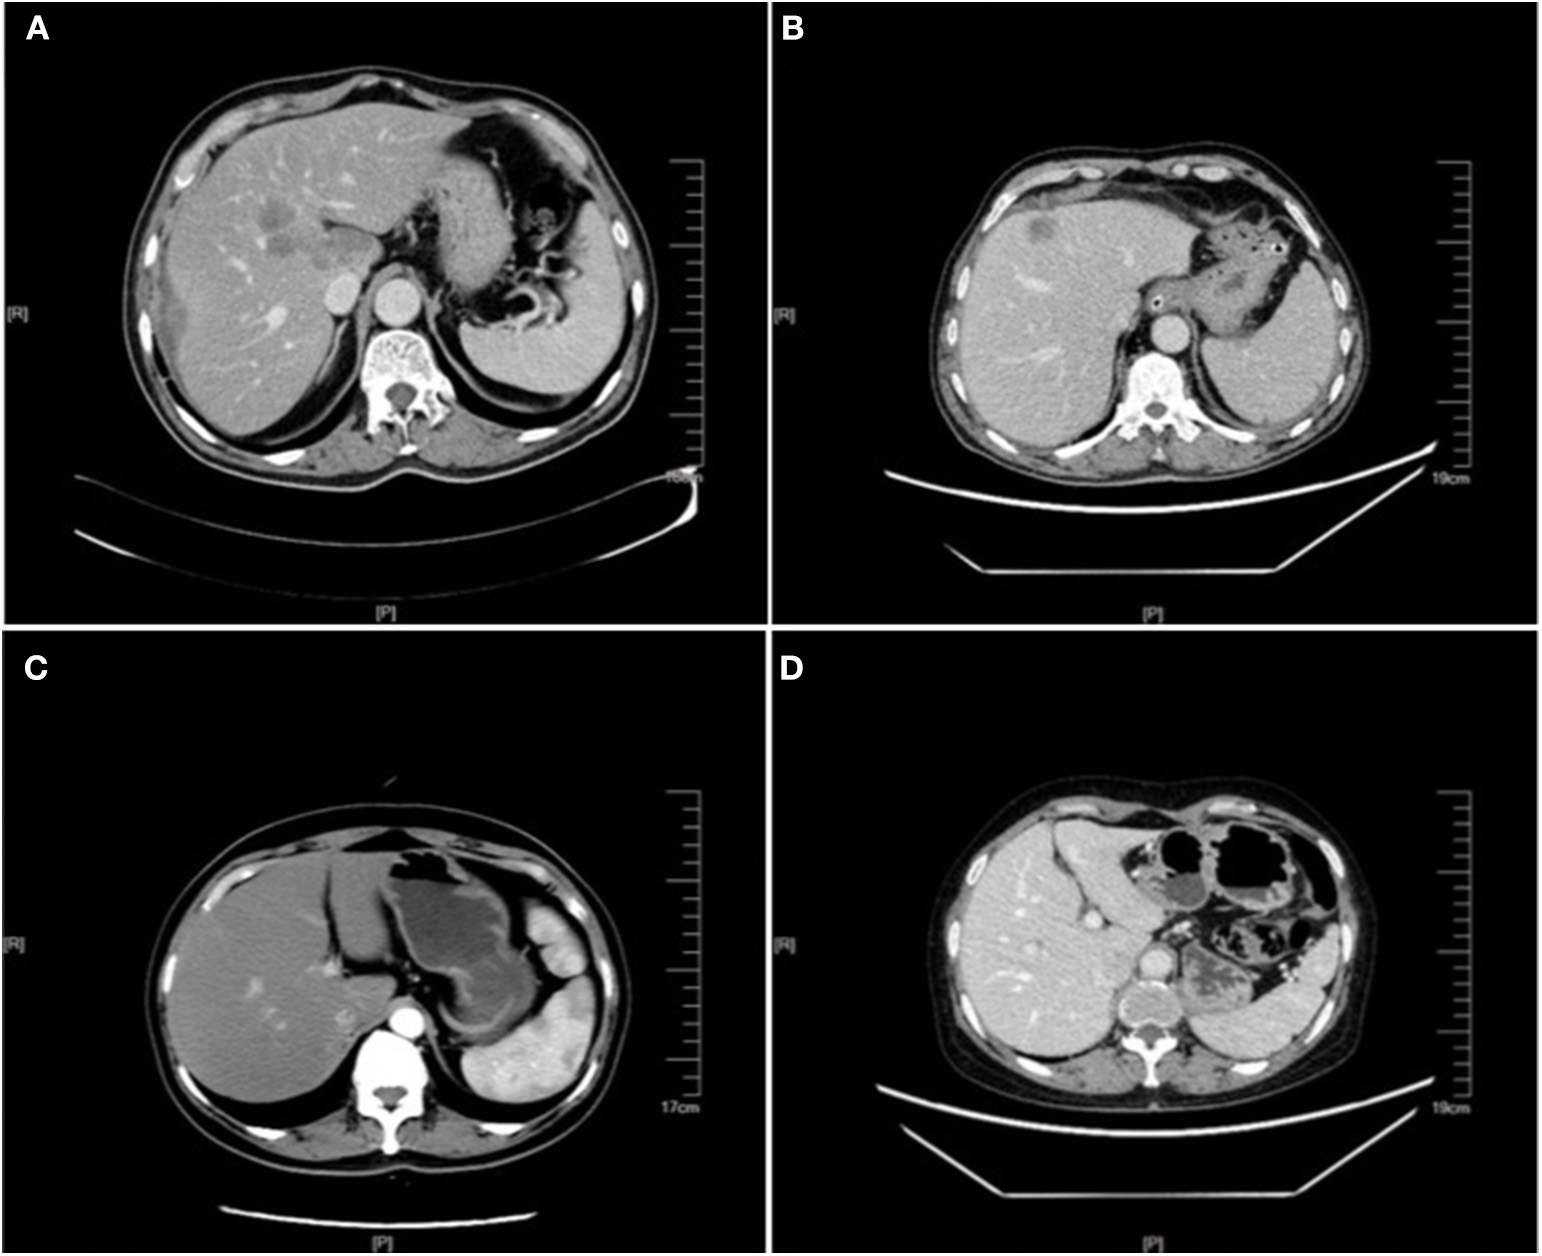
In high-risk patients, arterial phase hyperenhancement with portal/delayed washout on multiphase CT or MRI can diagnose HCC. Biopsy is used when imaging is indeterminate or the patient is not in a classic risk group.
Pros, cons and controversy
The controversy is not whether HCC surveillance matters, but whether it is done well.
Ultrasound can miss early HCC, especially with obesity or nodular cirrhosis. AFP creates false positives. But unlike many cancers, there is a clear high-risk group where repeated surveillance can shift stage and open transplant/ablation/resection options.
Sources and trials