progressive swallowing trouble is alarming.
Symptoms, risk, screening and diagnostic confirmation
Detect Esophageal Cancer is about choosing the right test for the right risk.
An esophageal cancer detection guide covering progressive dysphagia, reflux/Barrett's, endoscopy, biopsy, EUS, CT and PET-CT staging.
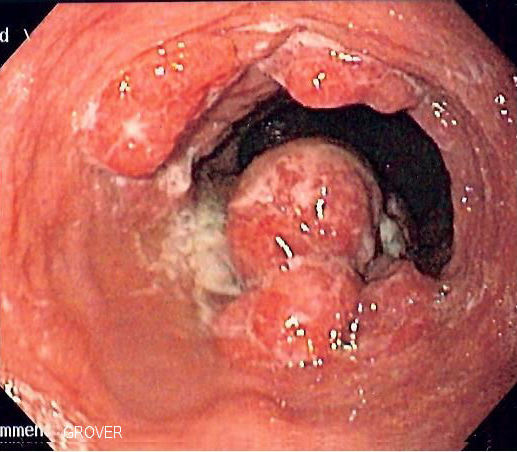
sees and biopsies lesions.
changes surveillance risk.
stage confirmed cancer.
Brief outline
What esophageal cancer means.
Esophageal cancer is usually adenocarcinoma near the gastroesophageal junction or squamous cancer higher in the esophagus. Progressive swallowing trouble is the red flag.
Detection frame
Screening is for people without symptoms. Diagnosis is for symptoms, abnormal examination, family history, imaging findings or abnormal labs. The same test can be sensible in one setting and misleading in another.
Do not ignore
Symptoms and signs not to ignore.
Risk and genetics
Demographics, risks and genetics.
Screening
Who should actually be screened?
Barrett's surveillance is risk-based; average-risk reflux alone is not the same as cancer screening.
Upper endoscopy
Directly examines and biopsies.
Biopsy/histology
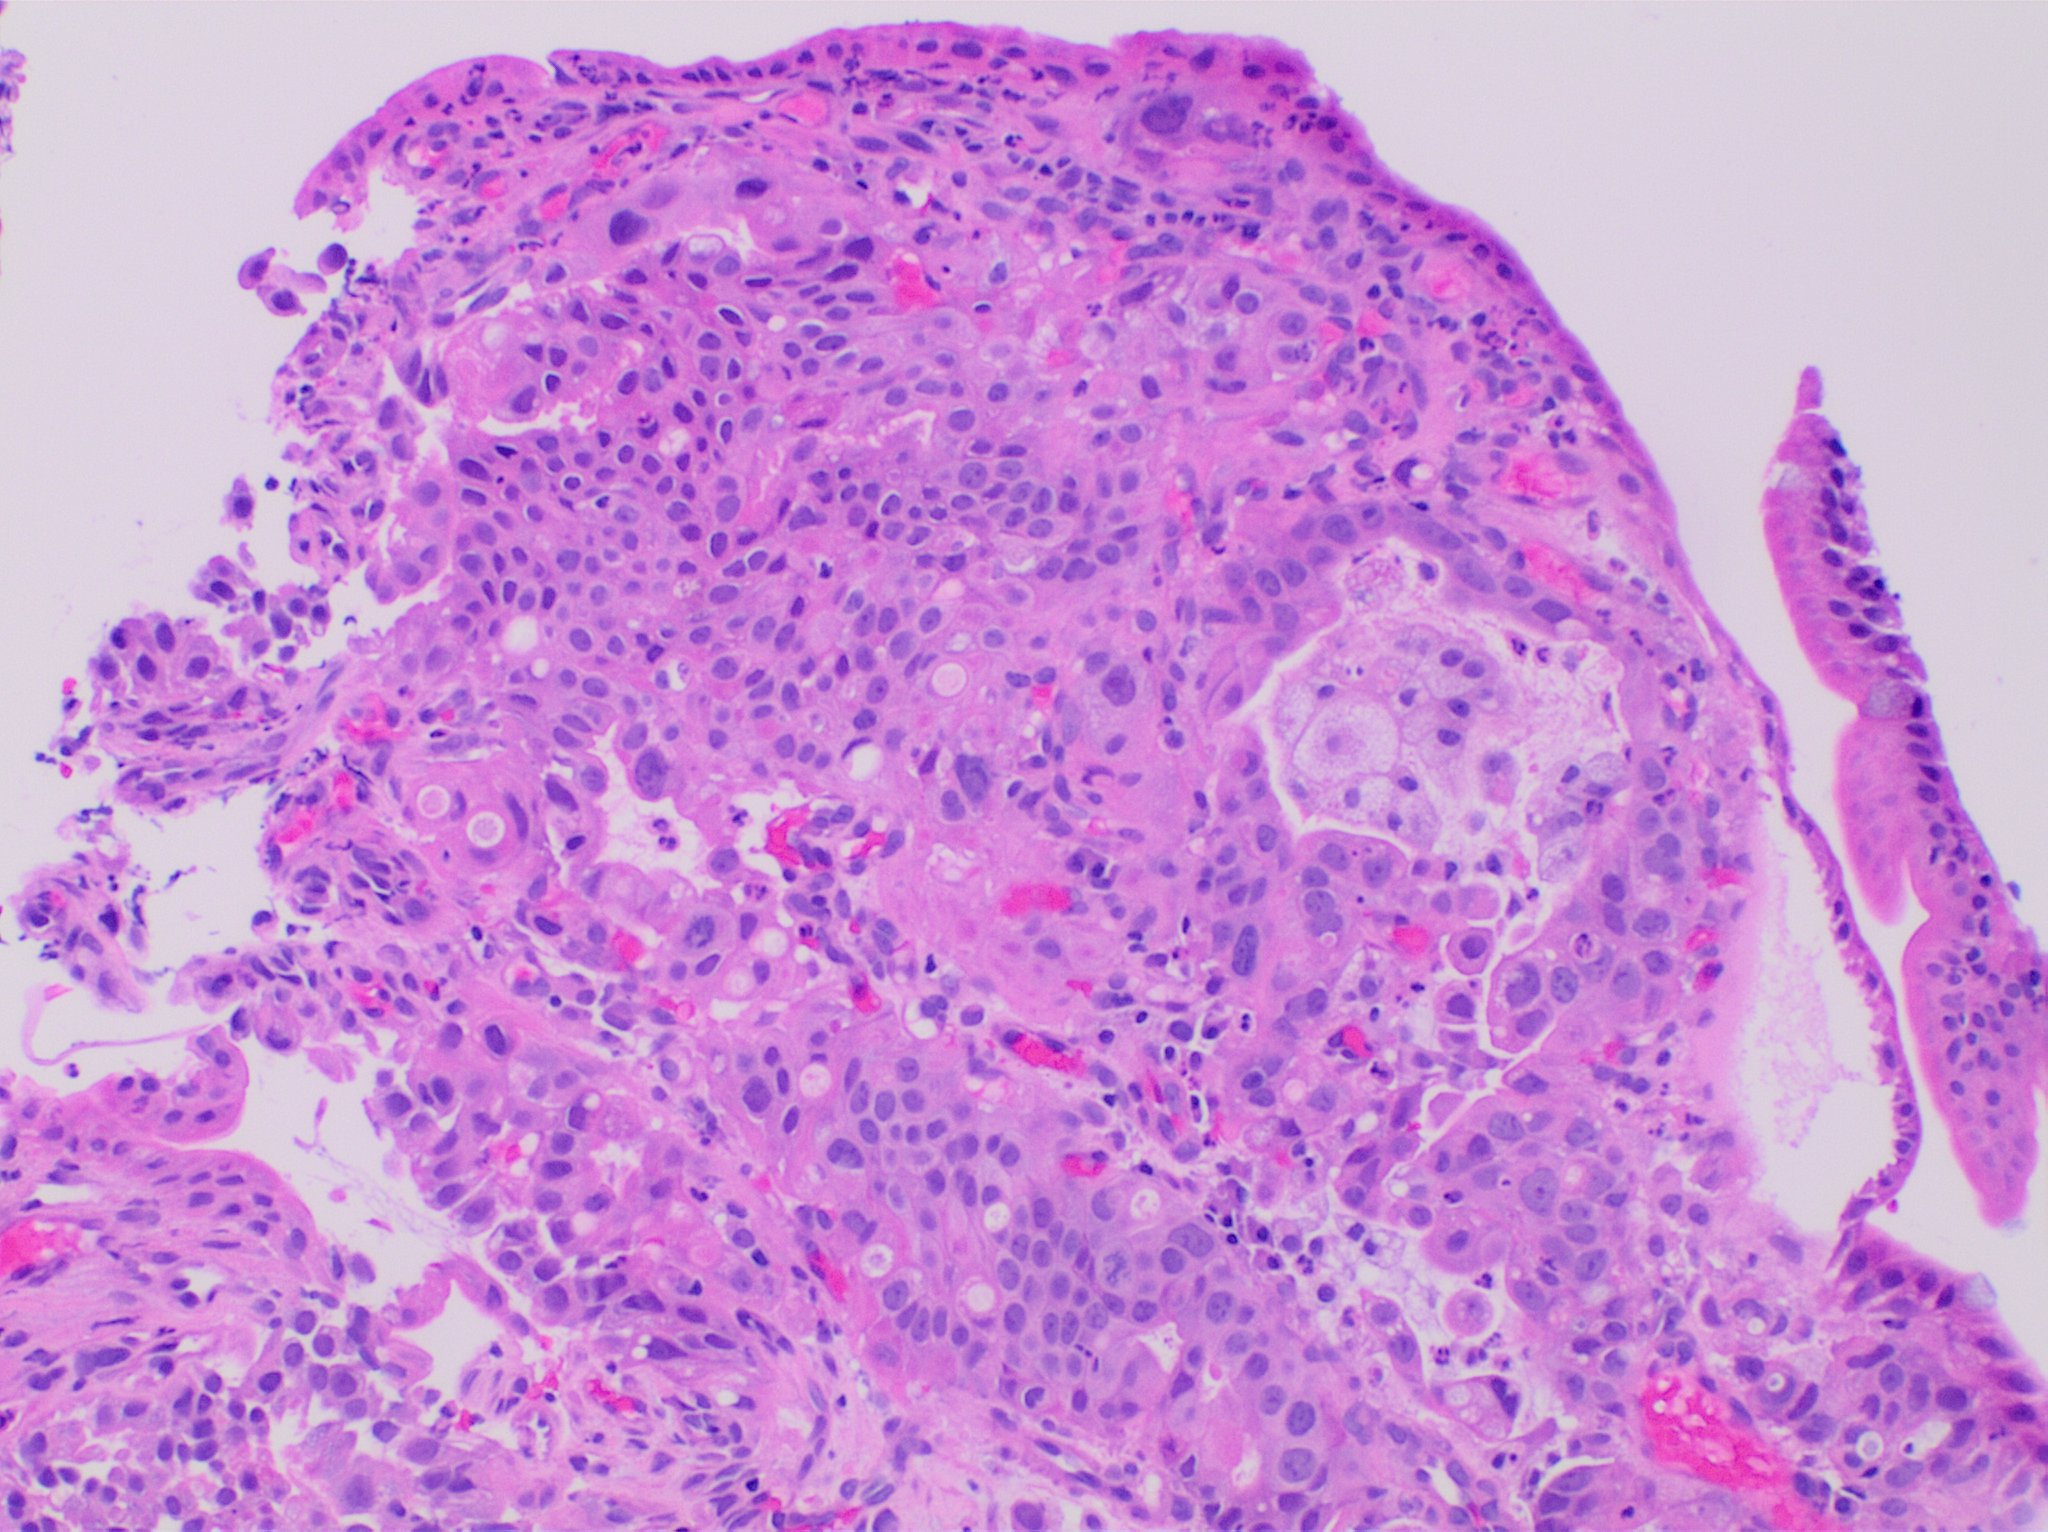
Confirms adenocarcinoma, SCC or dysplasia.
CT chest/abdomen
Assesses spread.
EUS
Helps T/N staging in selected cases.
PET-CT
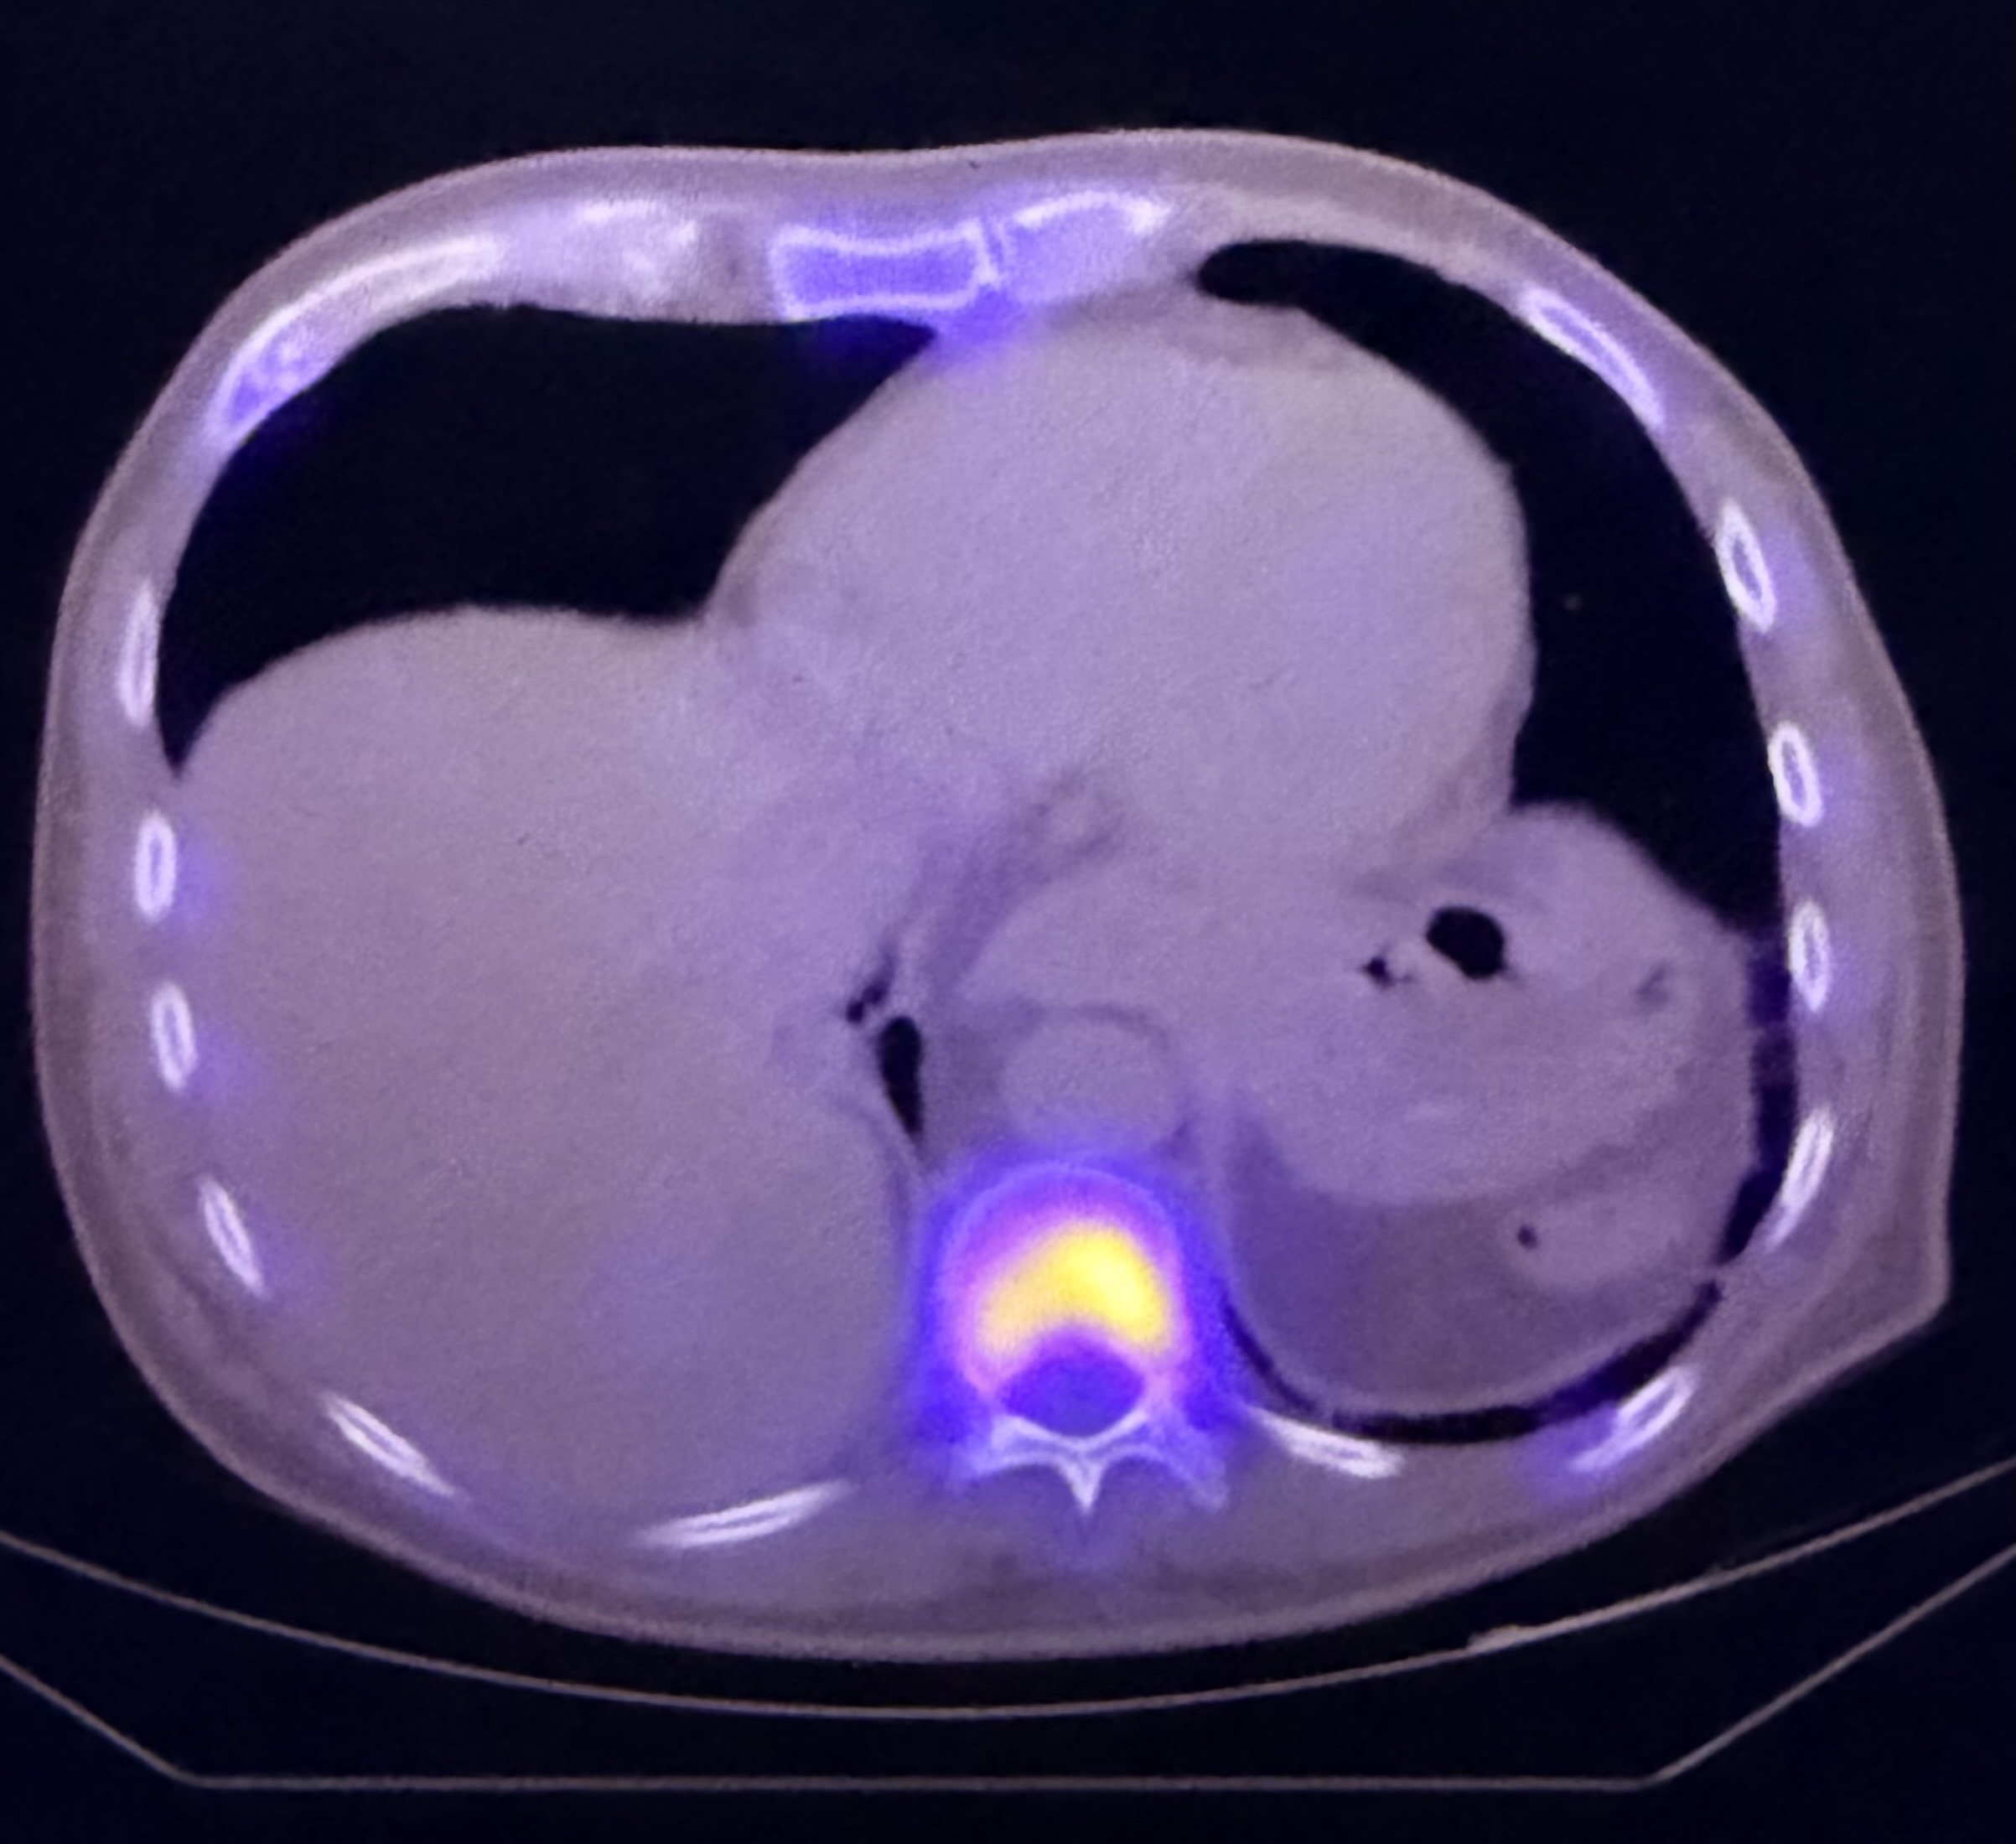
Looks for distant metastases.
Barium swallow
Useful for anatomy, but suspicious lesions still need endoscopy.
Images, labs and tissue
Useful tests and what they can miss.
Detection usually needs a chain: suspicion, imaging or lab triage, tissue or cytology when needed, then pathology and molecular testing where it changes management.
Pros, cons and controversy
Benefits, harms and the false-positive problem.
The benefit of Barrett's surveillance is focused risk management. The harm is over-scoping low-risk reflux without alarm features while missing progressive dysphagia.
Sources and trials